Acute pain is a messenger: you sprain an ankle, it swells, it hurts, it heals. Chronic pain is different. It persists for months or years — often long after the original injury has healed — because the nervous system itself has become sensitized. Understanding that shift is the first step toward beating it.
Pain Is an Output, Not Just an Input
Your brain decides when something hurts based on danger signals from tissues, but also on stress, sleep, past experience, and movement confidence. In chronic pain, the alarm gets stuck on: normal touch, ordinary movement, even sitting still can register as threatening. This is why scans often look "normal" while pain feels very real — the problem lives in sensitivity, not just structure.
The Four Drivers We Assess
- Stiff joints and guarded muscles — restricted segments force neighbors to overwork, spreading pain outward.
- Sensitized nerves — irritated neural tissue fires too easily; graded movement gradually desensitizes it.
- Deconditioning — months of avoidance weaken the very muscles that protect painful areas.
- Habits and load — posture, sleep, workload, and stress keep topping up the pain bucket daily.
Breaking the Loop
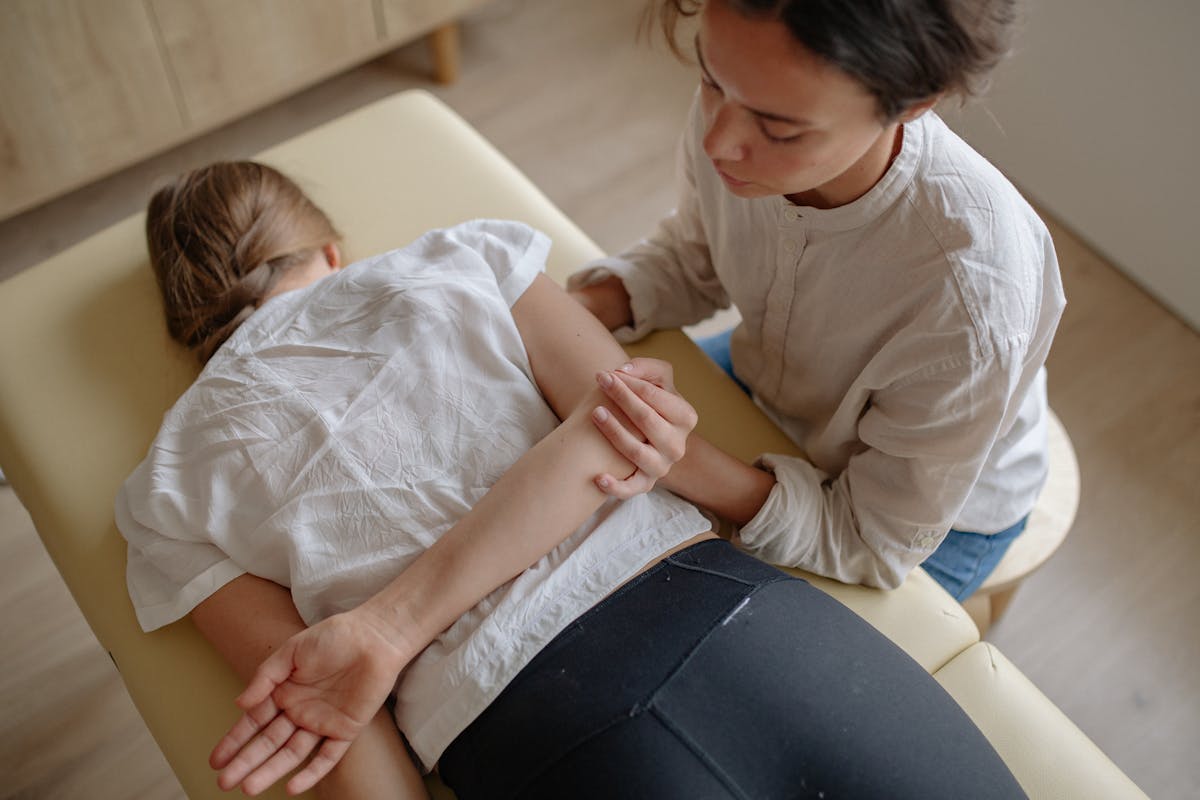
Effective chronic-pain care is layered. Manual therapy and modalities calm irritated tissue so you can move. Graded exercise rebuilds tolerance without flares. Education rewires the fear that keeps muscles guarded. None of these works alone — together, they lower the alarm step by step.

When to Seek Help
If pain has lasted more than three months, keeps returning to the same spot, or is shrinking your life — fewer walks, skipped workouts, guarded sleep — a structured program beats another round of waiting. Our pain management programs start with mapping your drivers, then calm, retrain, and sustain.
Pain may have moved in, but it doesn't get to stay. With the right plan, even years-old pain can quiet down — and stay quiet.